What is an inguinal hernia?
An inguinal hernia is a bulge in the groin where fat or a loop of bowel pushes through a weak area in the lower abdominal wall. It is the most common type of hernia. Studies estimate that about one in four men will develop one during their lifetime; it is much less common in women.
There are two main kinds. An indirect hernia follows the natural channel through which the testis descended before birth, and can extend down into the scrotum. A direct hernia pushes straight through a weakened patch of the wall, usually in older men. Both are repaired the same way.
Typical signs are a lump that appears when you stand, cough or lift and goes away when you lie down, a heavy or dragging feeling in the groin by evening, and aching after a long ride or a day of lifting. Some people have discomfort before any lump is visible. For an overview of all hernia types, see hernia surgery in Bangalore.
When do you need surgery?
An inguinal hernia does not close on its own. Whether you need surgery now depends on your symptoms, the type of hernia and your general health.
- Watchful waiting is reasonable for men with a small hernia that causes little or no discomfort. Large trials have found the risk of the hernia getting stuck is low in this group, though many of these men choose surgery within a few years as symptoms develop.
- Surgery is usually advised when the hernia aches, limits work or exercise, is getting bigger, or is hard to push back in.
- Women with a groin hernia are usually advised to have it repaired, preferably laparoscopically, because a femoral hernia (which has a higher risk of trapping) is more common in women and is easily missed.
Diagnosis: what happens at the consultation
Dr. Sanjit examines you standing and lying down and feels for a cough impulse on both sides. Most inguinal hernias are diagnosed this way without any scan.
An ultrasound of the groin is useful when the lump is small, when you have groin pain without a clear bulge, or to check the other side. It also helps tell a hernia apart from other groin swellings such as a lymph node, a hydrocele or a lipoma.
He then explains what he has found, whether waiting is safe for you, and which repair he recommends and why. If surgery is planned, routine blood tests and an ECG are arranged for anaesthesia fitness.
Treatment options: TEP, TAPP or open repair
Nearly all adult inguinal hernias are repaired with a mesh, which lowers the chance of recurrence compared with stitching alone. The difference between the options is how the mesh is placed.
| Technique | How it is done | Often suits |
|---|---|---|
| Laparoscopic TEP | Mesh placed behind the muscle without entering the abdominal cavity | Most first-time hernias, one or both sides |
| Laparoscopic TAPP | Surgeon enters the abdomen, lifts a flap of lining, places the mesh behind it and closes the flap | Large or scrotal hernias, previous lower abdominal surgery, unclear diagnosis |
| Open (Lichtenstein) | Single 5 to 8 cm groin cut, mesh stitched over the weak area | Patients better suited to spinal or local anaesthesia |
TEP and TAPP place the same kind of mesh in the same layer, covering all the weak points of the groin at once. International guidelines regard both as sound when done by a trained surgeon; the choice depends on your anatomy, previous surgery and the size of the hernia.
Dr. Sanjit's usual recommendation: for most working adults, a laparoscopic repair (TEP or TAPP) is the right fit, because most patients have less pain early on and return to work sooner. Open repair remains a good option if general anaesthesia is a concern, and it costs less.
Hernias on both sides: one operation, the same ports
Inguinal hernias on both sides (bilateral) are common. With laparoscopic repair, both sides are fixed in one operation through the same three small cuts, with one anaesthetic and one recovery. With open surgery, each side needs its own incision.
Laparoscopy also lets the surgeon look at the other side. Sometimes a small hernia is found there that was not felt on examination. Dr. Sanjit discusses before surgery what he will do if this happens, so you agree on the plan in advance.
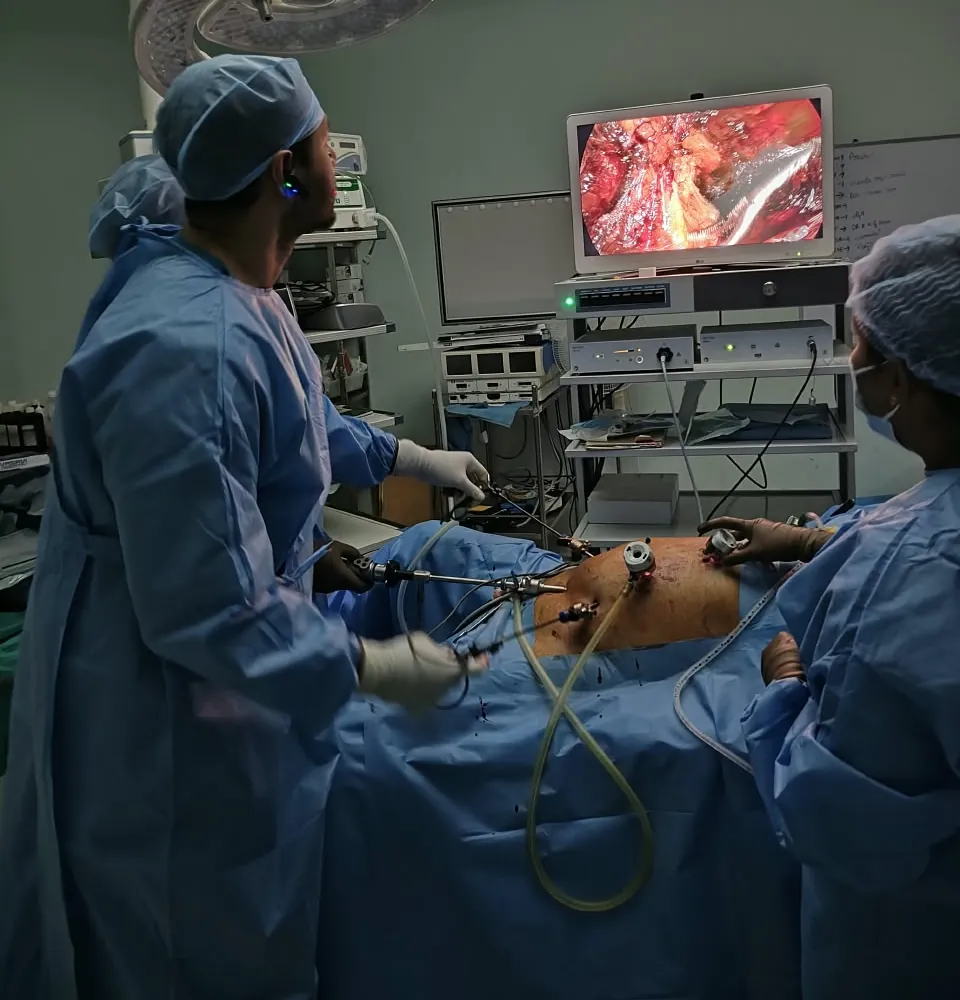
How laparoscopic inguinal hernia repair is done
- You are admitted on the day of surgery after fasting for about 6 hours, and are asked to pass urine just before going in.
- The operation is done under general anaesthesia.
- Three small cuts of 5 to 10 mm are made, one at or near the belly button and two below it.
- The hernia sac is gently pulled back and the groin area cleared, taking care of the nerves, blood vessels and, in men, the vas deferens (the tube that carries sperm).
- A mesh is laid flat over the weak areas with a generous overlap, and fixed with tacks or glue, or held in place by surrounding tissue, depending on the hernia.
- The cuts are closed with dissolvable stitches or skin glue.
One side usually takes about 45 to 90 minutes and both sides a little longer. Many patients go home the same evening or the next morning.
Recovery: what to expect
| Time | What most patients can do |
|---|---|
| Day 0–1 | Walk, eat, pass urine; home the same day or next morning |
| Days 2–7 | Walk several times a day; pain usually managed with tablets |
| About 1 week | Desk work and work from home |
| 1–2 weeks | Driving, once you can brake hard without pain |
| 2–4 weeks | Two-wheeler riding, gym with light weights, sexual activity when comfortable |
| 4–6 weeks | Heavy lifting and full sport, as advised |
Bruising in the groin and some swelling of the scrotum are common in the first week or two and settle on their own. A firm lump where the hernia was is often a seroma (a fluid pocket), not a recurrence, and usually disappears over a few weeks. Keep your bowels soft so you do not strain.
Groin pain and other risks
Some soreness after surgery is normal and fades over days to weeks. The risk most people ask about is long-term groin pain, defined as pain lasting more than three months.
Studies report that roughly 1 in 10 people have some lasting discomfort after inguinal hernia repair, and that pain severe enough to affect daily life is uncommon, affecting a small percentage. It is linked to irritation of the small nerves in the groin. Studies generally find it less frequent after laparoscopic repair than open repair.
To reduce the risk, Dr. Sanjit identifies and protects the nerves, avoids placing tacks in areas where nerves run, and uses glue or no fixation where that is safe. Pain that does not settle is assessed and treated, and most cases improve over time.
Other risks include:
- bruising, seroma and scrotal swelling, which are common and short-lived
- temporary difficulty passing urine, more often in older men
- infection, which is uncommon
- recurrence, reported in a few per cent of people after mesh repair
- rarely, injury to the bladder, bowel, blood vessels, the vas deferens or the blood supply of the testis
Inguinal hernia surgery cost in Bangalore
The cost depends mainly on whether the repair is laparoscopic or open, whether one or both sides are repaired, the type of mesh and fixation, and your hospital room category. Indicative 2026 ranges and insurance guidance are on the hernia surgery cost page.
Why patients from Sarjapur Road, HSR and Bellandur see Dr. Sanjit
Dr. Sanjit is a General and Minimal Access Surgeon with an MS in General Surgery, the MRCS from the Royal College of Surgeons of Edinburgh and about 18 years of surgical practice, including more than 6,000 procedures. Laparoscopic groin hernia repair, including recurrent hernias, is a core part of his work.
He sees patients at SPARSH Hospital, Sarjapur Road, from 10 am to 5 pm, where he also operates, and at his evening clinic in Doddakannelli from 5 pm to 8 pm, Monday to Saturday. Book a consultation or send your scan on WhatsApp first.

MBBS, MS (General Surgery), MRCS (Edinburgh). General and Minimal Access Surgeon with about 18 years in general, laparoscopic and laser surgery. Consults at SPARSH Hospital, Sarjapur Road (10 am – 5 pm) and his evening clinic in Doddakannelli (5 – 8 pm). KMC Reg. No. 96096. More about Dr. Sanjit